
As autumn leaves fall and daylight hours dwindle, many people notice a subtle shift in their energy and mood. The change escalates into Seasonal Affective Disorder (SAD), a type of depression that recurs annually, typically during the fall and winter months, only to lift with the arrival of spring. SAD isn’t just the “winter blues.” It’s a recognized medical condition that can significantly affect daily life, productivity, and overall well-being. Millions suffer worldwide, with higher prevalence in regions far from the equator where winters bring prolonged darkness. SAD’s impact on mental health is profound1 and our goal is to explore it in depth.
What is Seasonal Affective Disorder?
First identified in the 1980s by Norman Rosenthal, SAD is classified in the Diagnostic and Statistical Manual of Mental Disorders (DSM-5) as a major depressive disorder with a seasonal pattern.2 What sets SAD apart from other forms of depression is its predictable timing, often linked to changes in natural light exposure. This seasonality offers a unique window for prevention and early intervention. Prevalence estimates vary, but studies suggest it affects 1% to 9.7% of the population, depending on latitude and diagnostic tools used.3 For instance, in northern latitudes like Alaska or Scandinavia, rates can be higher due to extended periods of low sunlight. Interestingly, SAD isn’t limited to adults; it also appears in children and adolescents, highlighting the need for awareness across all ages.4
While symptoms like fatigue, oversleeping, and increased appetite for carbohydrates, area all tied to reduced sunlight exposure,6 research over the past four decades also reveals neurobiological factors like hormonal shifts and genetic predispositions that contribute.5 While the winter variant is predominant, affecting around 5% of the U.S. population in higher latitudes, a less common summer-onset form exists, potentially triggered by excessive heat and humidity.7
The disorder’s impact is profound: it can lead to social withdrawal, decreased productivity at work or school, and in severe cases, thoughts of suicide. Epidemiological studies reveal higher rates in northern regions, with variations across ethnic groups and even in younger populations.8 For example, a study in Aberdeen, Scotland, explored links between SAD and social deprivation, finding complex socioeconomic influences.9 Distinguishing SAD from milder seasonal mood fluctuations is crucial, as true SAD requires clinical attention to prevent chronic issues.
The research is fairly conclusive. Investigations show the biological underpinnings, such as melatonin dysregulation and serotonin imbalances are also significant contributors.10 Historically, SAD was met with skepticism. And although it’s now widely accepted, thanks to consistent findings from prospective population studies showing seasonal mood peaks in winter,11 for those who feel like hibernating through winter, it could be more than a passing feeling.
Potential Causes of SAD
The roots are multifaceted, blending biological, environmental, and genetic elements. At its core, reduced sunlight in winter disrupts the body’s internal clock and neurotransmitter balance, leading to depressive symptoms.12
Circadian Rhythm Disruptions
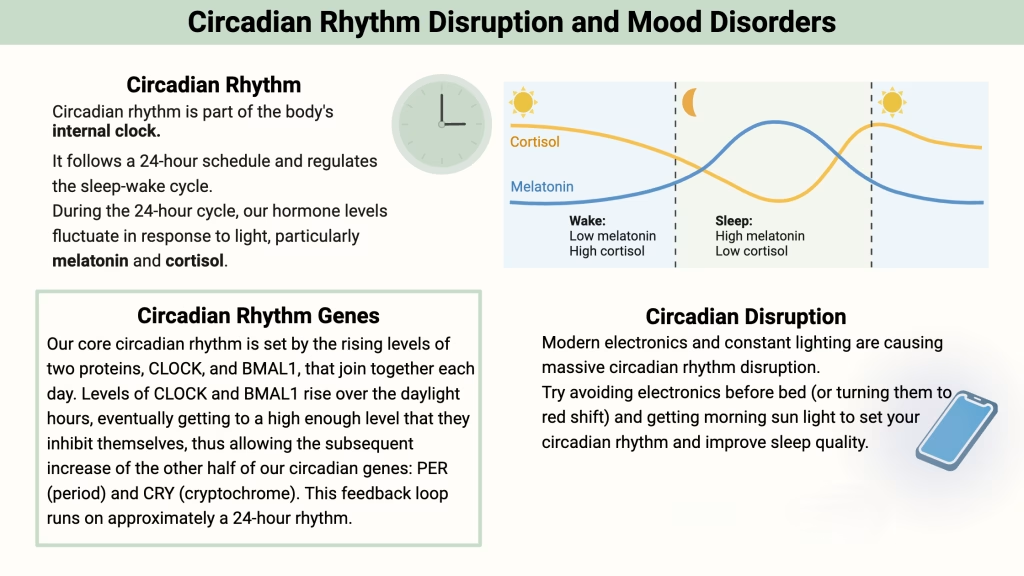 Your body’s circadian rhythm acts like an internal timer, regulating sleep, hormones, and mood over a 24-hour cycle. In winter, less sunlight can throw this rhythm off, delaying melatonin (the hormone that signals sleepiness) release and extending feelings of fatigue.13 Studies show that in SAD patients, this misalignment affects activity patterns and contributes to lethargy.14 Think of it as jet lag that lasts months: your body struggles to sync with the shorter days.
Environmental factors amplify this. Moving from a non-seasonal climate to one with stark winters increases SAD risk, suggesting an adaptation challenge.15 Additionally, the pineal gland, which produces melatonin, plays a key role. Abnormalities in its volume have been noted in mood disorders, including SAD.16 This gland’s function ties directly to light exposure, explaining why darker months disrupt rhythms.
Serotonin and Melatonin Imbalances
 Sunlight influences serotonin, a neurotransmitter that boosts mood. Reduced exposure lowers serotonin levels, while boosting melatonin, leading to excessive sleepiness and low energy.17 Primary research using PET scans reveals higher serotonin transporter levels in winter for SAD patients, correlating with symptom severity, especially in women with certain genetic profiles.17 Vitamin D deficiency, often from limited sun, may worsen this, though evidence varies.18
Melatonin, produced by the pineal gland, is central here. Studies on pineal peptides show they can restore hormonal balance, potentially aiding mood regulation.19 For instance, in animal models, epithalamin, alters circadian activity and reduces depression-like behaviors by modulating free radicals and hormones.20 This imbalance is like a chemical fog that lifts with more light or supportive interventions.
Genetic and Environmental Factors
 Genetics play a role; polymorphisms in serotonin-related genes heighten susceptibility.17 Family history is common, with up to 17% of SAD cases linked to relatives.21 Environmentally, higher latitudes mean greater risk due to shorter days.3 Lifestyle factors, like indoor time, exacerbate this.
Emerging research points to the gut-brain axis; gut peptides may influence mood via the microbiome.22 Negative life events and low social support also correlate with higher seasonality.23 Understanding these causes allows for tailored approaches, from lifestyle tweaks to targeted supplements.
The Symptoms: It’s Not Just Winter
 Seasonal Affective Disorder symptoms often mimic major depression but include unique seasonal twists. They typically build gradually in fall, peak in winter, and fade in spring.24 Core signs include persistent sadness, loss of interest in activities (anhedonia), and fatigue that makes everyday tasks feel monumental.9
Atypical features set SAD apart: hypersomnia (sleeping too much yet feeling unrested), intense carbohydrate cravings leading to weight gain, and increased irritability.25 Other symptoms might include difficulty concentrating, social withdrawal (often called “hibernating”) and, in severe cases, suicidal thoughts.1
For summer SAD (yes there’s summer SAD), symptoms flip to insomnia, appetite loss, and agitation.7
- Emotional Symptoms: Feeling hopeless or worthless most days.21
- Physical Symptoms: Low energy, heavy limbs, oversleeping.25
- Behavioral Changes: Overeating, especially sweets, avoiding social events.24
If symptoms persist beyond seasons, it might indicate non-seasonal depression.12 Studies also link SAD to personality traits and higher psychiatric morbidity.9 For example, someone with SAD might skip gym sessions they enjoyed in summer, compounding feelings of guilt. Recognizing these patterns early can lead to better outcomes.
Available Diagnoses of Seasonal Affective Disorder
The diagnosis involves a detailed clinical assessment to differentiate it from other conditions. Per DSM-5, it requires depressive episodes occurring in specific seasons for at least two years, with full remission in off-seasons and no non-seasonal episodes.2 Tools like the Seasonal Pattern Assessment Questionnaire (SPAQ) screen for seasonality.3
Physicians may perform exams to rule out hypothyroidism or vitamin deficiencies, and evaluate for comorbidities like anxiety.9 Untreated SAD can evolve into chronic depression, so early diagnosis is vital.24 Prevalence studies using different questionnaires show variations, emphasizing the need for standardized approaches.3
In practice, a doctor might ask about mood changes with seasons, sleep patterns, and family history. If you suspect SAD, tracking symptoms in a journal can aid diagnosis.
Common, Evidence-Based Treatments
Managing SAD often involves a combination of therapies tailored to individual needs. From light exposure to medications, options focus on symptom relief and prevention.4
Light Therapy
 Bright light therapy (BLT) is a cornerstone treatment, simulating sunlight to reset circadian rhythms and boost serotonin. Typically involving 10,000 lux for 30-60 minutes daily, preferably mornings, meta-analyses of RCTs confirm its efficacy, rivaling antidepressants.5 One study showed over 40% symptom reduction with white light.6 Natural outdoor walks can also help, as shown in trials.6
BLT is safe, with mild side effects like eye strain. It’s especially useful for those avoiding meds. Picture starting your day with a “sunrise” lamp—many report quicker mood lifts.10
Psychotherapy and Medications
 Cognitive Behavioral Therapy adapted for SAD (CBT-SAD) helps reframe negative thoughts about winter, providing lasting benefits over light therapy alone.7 RCTs show acute and long-term efficacy.8 Medications like SSRIs (fluoxetine) target serotonin, with trials demonstrating equivalence to BLT.11 Bupropion XL is FDA-approved for prevention, reducing recurrence.12
Combining therapies often yields best results. For adolescents, mirtazapine shows promise.13 Always consult a doctor for personalized plans.
Lifestyle Modifications
 Simple changes can make a big difference. Systematic reviews highlight benefits from exercise, outdoor time, balanced diet, and even music therapy.4 Vitamin D supplements may help if deficient.18 One study linked dark chocolate consumption to lower depression symptoms—perhaps due to mood-boosting compounds.14 Regular walks in daylight, healthy meals, and social activities combat isolation.
Exercise, like winter jogging, releases endorphins and improves sleep. Maintaining routines prevents symptom spirals.4
The Role of Bioregulators As a Supporting Tool
Bioregulators, also known as short-chain peptides, cytomaxes, or peptide bioregulators, are naturally occurring compounds extracted from specific organs or tissues, such as the pineal gland. These peptides work at a cellular level to modulate gene expression, promote repair, and restore balance in targeted systems.19 Unlike traditional medications that often target symptoms directly, bioregulators aim to support the body’s own regulatory mechanisms, potentially offering a gentler approach with fewer side effects.
For those dealing with Seasonal Affective Disorder, pineal-derived bioregulators hold particular promise because of the pineal gland’s central role in regulating circadian rhythms and melatonin production.
To put it simply, think of bioregulators as “messengers” that help fine-tune your body’s internal clock and hormone levels. In the context of SAD, where shorter days lead to overproduction of melatonin and underproduction of serotonin, these peptides could help recalibrate these imbalances. Research on pineal peptides, such as the synthetically-derived epitalon, has shown it can restore age-related disturbances in hormonal functions, including those of the pineal gland itself.20 This restoration might extend to seasonal disruptions, as the pineal gland’s output of melatonin is heightened in winter, contributing to the lethargy and low mood characteristic of SAD.
Primary studies in animal models provide intriguing evidence. For instance, chronic administration of pineal peptides found in products like our Pineal Bioregulators has been found to alter circadian locomotor activity, shifting activity patterns and increasing amplitude in rats with low initial rhythms. This mirrors the potential benefits for humans with disrupted sleep-wake cycles in SAD.26 Moreover, these types of peptides and bioregulators reduced the “rhythmic index of depression” in forced swimming tests, a common model for assessing depression-like behaviors. This suggests that Promethean’s Pineal Bioregulators may prevent or mitigate depressive states by stabilizing circadian functions and reducing oxidative stress or inflammation that exacerbates mood issues.26 Another study highlights how pineal peptides influence free radical processes and hormonal balance, which could indirectly support mood by countering the oxidative damage linked to chronic stress and seasonal changes.19

Human studies are more limited, as bioregulators are still considered experimental for mood disorders like SAD. However, their use in aging and endocrine research shows favorable safety profiles, with no significant adverse effects reported in controlled trials.20 It is important to note that these studies hold promise but are primarily from preclinical or small-scale studies. There certain, more rigorous clinical trials underway to confirm true efficacy for SAD specifically, and overall depression, generally.
As noted, bioregulators are not a cure-all and should be used in conjunction with additional supportive methods, not replacements.
At Promethean Bioregulators, our Pineal Bioregulator is designed to support pineal gland function, potentially aiding in mood stability and circadian rhythm regulation during the challenging winter months. We derived our bioregulators from high-quality sources and formulated for optimal absorption. We offer a supportive, complementary option for those exploring natural ways to enhance well-being. As with any supplement, consult your healthcare provider before incorporating it, particularly if you have existing conditions or are taking medications that affect hormones or mood.
Conclusion
Seasonal Affective Disorder, while challenging, is highly manageable. By understanding its causes and recognizing symptoms early, you can employ effective treatments like light therapy, CBT, medications, and lifestyle changes. Innovative options like bioregulators offer additional support for mood balance, particularly through pineal health.
If SAD affects you, don’t be afraid to reach out to a professional. Brighter days are within reach, no matter the season.
For more on optimizing health with bioregulators, visit Promethean Bioregulators.
References
- An overview of epidemiological studies on seasonal affective disorder
- Prevalence of seasonal affective disorder in primary care; a comparison of the seasonal health questionnaire and the seasonal pattern assessment questionnaire
- Prevalence of seasonal affective disorder at four latitudes
- Lifestyle modification as intervention for seasonal affective disorder: A systematic review
- The Efficacy of Light Therapy in the Treatment of Seasonal Affective Disorder: A Meta-Analysis of Randomized Controlled Trials
- Bright light treatment of winter depression: a placebo-controlled trial
- Outcomes One and Two Winters Following Cognitive-Behavioral Therapy or Light Therapy for Seasonal Affective Disorder
- Randomized Trial of Cognitive-Behavioral Therapy Versus Light Therapy for Seasonal Affective Disorder: Acute Outcomes
- Seasonality is associated with anxiety and depression: the Hordaland health study
- ‘Natural’ light treatment of seasonal affective disorder
- The Can-SAD study: a randomized controlled trial of the effectiveness of light therapy and fluoxetine in patients with winter seasonal affective disorder
- Seasonal affective disorder and its prevention by anticipatory treatment with bupropion XL
- Mirtazapine in the treatment of adolescents with major depression: an open-label, multicenter pilot study
- Is there a relationship between chocolate consumption and symptoms of depression? A cross-sectional survey of 13,626 US adults
- Effect of Hometown Seasonality on Undergraduate Students’ Risk of Developing Seasonal Affective Disorder
- Pineal Abnormalities in Psychosis and Mood Disorders: A Systematic Review
- Brain Networks Implicated in Seasonal Affective Disorder: A Neuroimaging PET Study of the Serotonin Transporter
- Vitamin D supplementation for treatment of seasonal affective symptoms in healthcare professionals: a double-blind randomised placebo-controlled trial
- Peptides of pineal gland and thymus prolong human life
- Pineal peptides restore the age-related disturbances in hormonal functions of the pineal gland and the pancreas
- Seasonal and Nonseasonal Depression: How Do They Differ? Symptom Profile, Clinical and Family History in a General Population Sample
- Anxiety, Depression, and the Microbiome: A Role for Gut Peptides
- Seasonality, negative life events and social support in a community sample
- Seasonality in depressive and anxiety symptoms among primary care patients and in patients with depressive and anxiety disorders; results from the Netherlands Study of Depression and Anxiety
- Seasonal alteration in taste detection and recognition threshold in seasonal affective disorder: the proximate source of carbohydrate craving
- Chronic administration of pineal peptides change the circadian locomotor activity and time-course of forced swimming in rats
