
Raynaud’s Disease, also known as Raynaud’s Phenomenon or Raynaud’s Syndrome, is a common yet often misunderstood condition that affects blood flow to the extremities, particularly the fingers and toes. Triggered by cold temperatures or emotional stress, it leads to episodes of vasospasm where blood vessels narrow dramatically, causing discomfort, color changes, and potential complications. While mostly not life-threatening, it can significantly disrupt daily activities and quality of life. The following information is educational. As always, consult a healthcare professional for personalized guidance.[1][2]
What is Raynaud’s Disease?
 Raynaud’s Disease is characterized by episodic vasospasms, the sudden and inappropriate constriction of arteries. The narrowing of the blood vessels and reduced blood flow to the small arteries and arterioles of the extremities, results in a classic triphasic color change: pallor (white) from ischemia, cyanosis (blue) from deoxygenation, and rubor (red) from reactive hyperemia upon rewarming.[1][3]
There are two primary forms: Primary Raynaud’s, which occurs independently without an associated disease, and Secondary Raynaud’s, linked to underlying conditions such as autoimmune disorders like scleroderma or lupus.[4]
Primary Raynaud’s accounts for about 80-90% of cases and is generally benign, while secondary forms can be more severe and require investigation into the root cause.[5]
The condition was first described by Maurice Raynaud in 1862, and since then, research has highlighted its vascular and neurological components. Understanding the distinction between primary and secondary is crucial, as management strategies differ.[4]
Prevalence, Trends, and Impact of Raynaud’s Disease
 Raynaud’s Disease affects approximately 3-5% of the general population worldwide, with higher rates in colder climates and among women, who are affected up to nine times more frequently than men.[6][5][7] In the United States, prevalence estimates range from 4.9-20.1% in women and 3.8-13.5% in men, varying by ethnicity and geography.[8] For instance, studies show higher incidences in Northern Europe compared to warmer regions. Among those with autoimmune diseases, such as scleroderma, up to 90% experience Raynaud’s as a symptom.[5]
 Recent trends from 2020-2025 indicate stable incidence rates, with no significant rise or fall in overall prevalence, though seasonal peaks in hospitalizations occur during colder months, such as January.[6] The global market for Raynaud’s treatments has grown, reflecting increased awareness and diagnostic efforts rather than a surge in cases. Theories for any perceived increases include better reporting, environmental factors like climate change affecting temperature extremes, and lifestyle changes such as increased stress levels in modern society.[9] However, core incidence remains consistent, emphasizing the need for ongoing education and management strategies.
The impact extends beyond physical discomfort; many individuals report anxiety about triggers, limitations in outdoor activities, and occupational challenges, particularly in professions involving cold exposure or vibration.[9] Early diagnosis can mitigate long-term effects like digital ulcers in severe cases.
Symptoms of the Raynaud’s Phenomenon
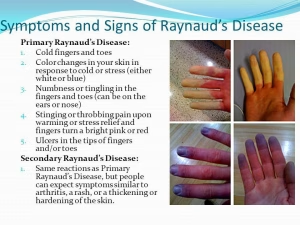 Raynaud’s Disease symptoms typically manifest during attacks, lasting from a few minutes to hours. The sequence begins with fingers or toes turning white due to constricted blood vessels, followed by blue discoloration as oxygen depletes, and ending with red as blood rushes back, often accompanied by throbbing pain, numbness, or tingling.[1][10] Less commonly, the nose, ears, or lips may be affected. Triggers include cold air, water, or even holding a cold object, as well as emotional stress.[2]
In severe or secondary cases, prolonged ischemia can lead to skin sores, ulcers, or tissue damage. Monitoring symptoms through a diary can help identify patterns and inform treatment.[4]
Causes, Risk Factors, and Theories
The precise cause of primary Raynaud’s Disease is unknown, but it involves an exaggerated vascular response to stimuli. The sympathetic nervous system plays a key role, releasing neurotransmitters that cause vasoconstriction.[11][9] Genetic factors have been identified, including variations in the ADRA2C gene and IRX1 gene, increasing susceptibility.[5]
Risk factors include female gender, family history, smoking (which impairs circulation), and repetitive trauma from tools or typing.[9] For secondary Raynaud’s, autoimmune diseases, medications, or occupational exposures are culprits.[11]
Theories posit disruptions in the nervous system’s control of blood vessels, possibly due to autoimmune targeting of vascular endothelium.[10] Imbalances in vasoactive peptides like endothelin-1 (vasoconstrictor) and calcitonin gene-related peptide (CGRP, vasodilator) are implicated.[12][13] Central nervous system involvement is evident, as stress triggers amplify sympathetic responses.[9]
Traditional Treatments and Supplementation for Raynaud’s
 Treatment begins with non-pharmacological measures. Lifestyle modifications include wearing layered clothing, gloves, and hats in cold weather; using hand warmers; avoiding caffeine and nicotine, which constrict vessels; and managing stress through mindfulness, yoga, or biofeedback training.[14][15] Regular exercise promotes circulation, while protecting hands from trauma is essential.[15]
For moderate symptoms, medications like calcium channel blockers (e.g., nifedipine) relax blood vessels and are first-line therapy.[16] Other options include topical nitrates, alpha-blockers, or phosphodiesterase inhibitors like sildenafil for vasodilation.[16] In severe cases, especially secondary Raynaud’s, immunosuppressants or antiplatelet agents may be used if linked to autoimmune issues.[16]
Complementary therapies show promise: acupuncture has demonstrated efficacy in mild cases by modulating autonomic responses,[17] while ginkgo biloba may improve circulation.[18] Surgery, such as sympathectomy to interrupt nerve signals, is reserved for refractory cases.[15] Monitoring for complications like ulcers involves wound care and antibiotics if needed.
 Beyond well-known options like ginkgo biloba, other supplements are being explored for their potential in supporting vascular health in Raynaud’s. Turmeric, or its active compound curcumin, has shown promise in preliminary observations. In a 2024 study involving patients with systemic sclerosis (often associated with secondary Raynaud’s), curcumin was among phytopharmaceuticals used, with participants reporting improvements in Raynaud’s symptoms, likely due to its anti-inflammatory and vasodilatory properties.[19] While not a standalone treatment, curcumin’s ability to modulate inflammation could complement other strategies, though more targeted research on Raynaud’s is needed.
It’s important to note that supplements like turmeric should be approached cautiously, as they can interact with medications. Starting with dietary sources or low-dose supplements under medical guidance may help gauge benefits for circulation without risks.
Advanced Alternative Therapies for Raynaud’s
 Alternative therapies offer additional avenues for those seeking non-pharmacological support for Raynaud’s Disease. Low-level laser therapy (LLLT), often referred to as red-light therapy, has demonstrated efficacy in reducing the frequency and severity of Raynaud’s attacks. Multiple studies from the early 2000s show that LLLT improves blood flow and symptoms in both primary and secondary forms, with effects lasting in the short to medium term.[20][21][22][23] This therapy uses light to stimulate cellular energy and vasodilation, making it a safe, non-invasive option for home or clinical use.
Ozone therapy, involving the administration of ozone gas, has emerged as a potential aid for Raynaud’s, particularly in treating associated ulcers. A 2022 study found major autohemotherapy with ozone provided rapid and sustained relief from symptoms, while another noted benefits for digital ulcers in systemic sclerosis patients.[24][25] Ozone may enhance oxygenation and reduce inflammation, but it’s experimental and requires professional administration.
Hyperbaric oxygen therapy (HBOT), where patients breathe pure oxygen in a pressurized chamber, has been used for severe cases, especially ulcers. Recent reports from 2021-2022 indicate HBOT improves circulation and heals ischemic ulcers in Raynaud’s linked to systemic sclerosis.[26][27][28] This therapy boosts tissue oxygenation, potentially alleviating vasospasms, though sessions are intensive.
Electrostimulation, such as spinal cord or transcutaneous electrical nerve stimulation (TENS), shows promise for refractory Raynaud’s. Studies spanning 1980s to 2020 report reduced attack frequency and improved blood flow, with spinal cord stimulation particularly effective for severe cases.[29][30][31][32][33] It modulates nerve signals to promote vasodilation.
 HOCATT therapy (a multi-modal approach combining ozone, hyperthermia, and other elements) may also theoretically support circulation. While specific studies on Raynaud’s are lacking in primary literature, general ozone and hyperbaric benefits do apply. We would recommend a consult with specialists for tailored use.[25][27]
Bioregulators – An Effective and Supportive Complement
Bioregulators represent an innovative approach to supporting organ-specific functions. These tiny peptides mimic endogenous ones, potentially aiding in cellular regulation and restoration.[13] In Raynaud’s, peptides like CGRP have been studied for their vasodilatory effects, with infusions showing prolonged benefits in severe ischemia.[34][35]
Research indicates CGRP deficiency may contribute to vasospasms, and targeting this pathway could improve microcirculation.[13][36] Other peptides, such as those influencing vascular endothelium, may address imbalances in endothelin-1 and promote healthy vessel tone.[12]
 The Blood Vessel Bioregulator (Ventfort or A-3 Peptide Complex) contains short peptides from vascular tissues, potentially supporting protein synthesis and circulation. Users report enhanced comfort in cold conditions, though research is emerging.
 Given the nervous system’s role, the Central Nervous System Bioregulator (Cerluten or A-5 Peptide Complex) may offer additional support by targeting peptides that regulate sympathetic responses and stress-induced vasospasms.[36]
 Finally, the Cartilage Bioregulator (Sigmuir or Peptide Complex A-4) supports regenerative protein synthesis in the smaller connective tissues, allow a reset at the cellular level to enhance circulation and lessen pain.
The naturally-derived and purified cytomaxes are dietary supplements, with no major side effects reported in studies. While they are still experimental for Raynaud’s, integrate a daily (one capsule, each) approach under medical supervision to complement traditional care.[37]
Conclusion
Raynaud’s Disease doesn’t have to dominate your life. With a blend of lifestyle changes, traditional treatments, supplements like turmeric, and alternative therapies such as red-light or hyperbaric oxygen, alongside innovative supports like bioregulators, you can foster better vascular health. Remember, while these options show promise, they’re most effective when personalized, discuss with your doctor to find what works for you.
References
- Raynaud’s phenomenon: from molecular pathogenesis to therapy
- Raynaud’s phenomenon
- [Differential diagnoses of Raynaud’s phenomenon]
- Raynaud Phenomenon
- Primary Raynaud’s phenomenon. Age of onset and pathogenesis in a prospective study of 115 patients
- Prevalence, risk factors and associations of primary Raynaud’s phenomenon: systematic review and meta-analysis of observational studies
- Prevalence of primary Raynaud’s phenomenon in young females
- The prevalence of Raynaud’s phenomenon: a critical review
- Raynaud’s Phenomenon: A Brief Review of the Underlying Mechanisms
- Raynaud’s phenomenon
- Raynaud’s phenomenon
- Calcitonin gene-related peptide, endothelin-1, the cutaneous microcirculation and Raynaud’s phenomenon
- Deficiency of calcitonin gene-related peptide in Raynaud’s phenomenon
- Treatment of Raynaud’s phenomenon: new insights and developments
- The diagnosis and treatment of Raynaud’s phenomenon: a practical approach
- Pharmacotherapy of Raynaud’s phenomenon
- Treatment of Raynaud’s phenomenon by fibrinolytic enhancement
- Ginkgo biloba extract for the treatment of intermittent claudication: a meta-analysis of randomized trials
- Patients with systemic sclerosis frequently use phytopharmaceuticals
- Low level laser therapy in primary Raynaud’s phenomenon
- Low level laser therapy for treatment of primary and secondary Raynaud’s phenomenon
- Double-blind, randomised, placebo controlled low level laser therapy study in patients with primary Raynaud’s phenomenon
- Low level laser treatment of primary and secondary Raynaud’s phenomenon
- Rapid and Sustained Effect of Ozone Major Autohemotherapy for Raynaud’s Phenomenon
- Non-invasive Oxygen-Ozone Therapy in Treating Digital Ulcers of Systemic Sclerosis Patients
- Treatment of Raynaud phenomenon and ischemic ulcers associated with systemic sclerosis
- [Potentiating the regional effect of hyperbaric oxygenation in Raynaud’s disease]
- Multidisciplinary Treatment for Severe Secondary Raynaud’s Phenomenon
- A case of spinal cord stimulation in Raynaud’s Phenomenon
- The Complementary Effects of Galvanic Current Electrical Stimulation on Symptoms Associated with Raynaud’s Phenomenon
- Transcutaneous electrical nerve stimulation (TENS) in Raynaud’s phenomenon
- Spinal cord stimulation for the treatment of progressive systemic sclerosis and Raynaud’s syndrome
- Clinical and objective data on spinal cord stimulation for the treatment of severe Raynaud’s disease: 14-year follow-up
- Calcitonin gene-related peptide in treatment of severe peripheral vascular insufficiency in Raynaud’s phenomenon
- Prolonged effect of CGRP in Raynaud’s patients: a double-blind randomised comparison with prostacyclin
- Raynaud’s phenomenon associated with calcitonin gene-related peptide-targeting drugs
- Evaluation of the Safety of Calcitonin Gene-Related Peptide Antagonists for Migraine Treatment Among Adults With Raynaud Phenomenon
