
Desiccated thyroid vs bioregulator is a comparison people make constantly, and it falls apart the moment you read the label. One is a prescription hormone drug measured in micrograms of T4 and T3. The other is a peptide complex with no thyroid hormone in it at all. Below we simplify the comparison, show what the research says, and why the difference matters more than the word “natural.”
By the Promethean Bioregulators Team | Published August 2026
Start With What Is In The Bottle
Most arguments about thyroid support fall apart because nobody checks the label first.
Open a bottle of desiccated thyroid and you are holding a hormone drug. The Armour Thyroid prescribing information states that each grain provides 38 mcg of levothyroxine (T4) and 9 mcg of liothyronine (T3).1 One grain weighs 60 to 65 mg depending on the brand, so the remaining 59-plus milligrams are the rest of the gland: thyroglobulin fragments, calcitonin, connective tissue.
Open a our Thyroid Bioregulator box and you are holding a short peptide fraction isolated from thyroid tissue. There is no T4 figure on the label because there is no T4 in it.
That is the entire comparison in one paragraph. Everything below is why it matters.

A Sixty-Second Map Of Thyroid Function
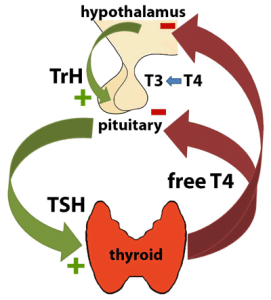 The thyroid is a small butterfly-shaped gland at the base of the neck. Follicular cells take up iodide, attach it to thyroglobulin using the enzyme thyroperoxidase, and produce thyroxine (T4) and triiodothyronine (T3).
One detail is worth holding onto. T4 is made exclusively by the thyroid, under the control of thyroid-stimulating hormone from the pituitary. T3, the more active form, is only partly made in the gland and is generated to a much larger extent in other tissues by enzymes that strip an iodine atom off T4. That proportion is not fixed. It shifts depending on conditions.2
The whole loop runs on feedback. The pituitary releases TSH, TSH tells the gland to produce, rising hormone tells the pituitary to ease off. When the gland is damaged, under stimulated, iodine-starved, or under autoimmune attack, that conversation breaks down.
Two very different product philosophies grew out of that physiology. Supply the missing hormones. Or support the tissue that is supposed to make them.
Desiccated Thyroid: A Hormone Replacement Drug
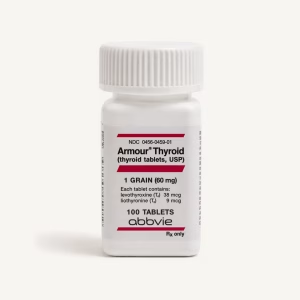 Desiccated thyroid extract is cleaned, dried, powdered thyroid gland, almost always porcine in modern US products. It is a prescription drug. It is dosed against labs and titrated by a clinician.
Working from the label figures, the T4 to T3 ratio in the tablet is roughly 4 to 1. That is considerably more T3, relative to T4, than the human thyroid itself secretes, since most circulating T3 is produced outside the gland rather than in it.2 People who feel better on desiccated thyroid frequently point to the T3. Endocrinologists point at the same T3 for the opposite reason.
What The Two Best Trials Found
Two randomized, double-blind crossover studies carry most of the weight here, and both are worth reading rather than summarizing.
Hoang and colleagues switched 70 adults with primary hypothyroidism between desiccated thyroid and levothyroxine in 2013. Symptom scores and neurocognitive measurements did not differ between the two therapies. What did differ was preference: 48.6 percent preferred desiccated thyroid, 18.6 percent preferred levothyroxine, and 32.9 percent had no preference. Patients lost roughly three pounds on the extract.3
Shakir and colleagues ran a three-way crossover in 2021 across levothyroxine, levothyroxine plus liothyronine, and desiccated thyroid. Across the full group the primary outcomes were similar. The finding that mattered was in the subgroup: the most symptomatic patients on levothyroxine alone tended to prefer and improve on the arms containing T3.4
That is a fair reading. Desiccated thyroid is not a miracle and it is not inert, and a subset of people who still feel unwell on T4-only therapy prefer something that contains T3.
It is also why the American Thyroid Association task force concluded that levothyroxine should remain the standard of care, finding no consistently strong evidence for the superiority of alternative preparations.5 Preference and superiority are not the same claim, and the guideline is answering the second question.
The Practical Point
Because desiccated thyroid contains preformed T3, dosing errors show up as hormone excess rather than as a mild supplement side effect. That is the reason it belongs in a clinician’s hands and on a lab schedule.
It is also the reason nobody should change a prescription because of an article. Not this one, not any other.
The Thyroid Cytomax: A Tissue-Signal Supplement
 Cytomax is a manufacturing class, not a hormone. In the Khavinson lineage, these are peptide complexes isolated from the organs of young animals, enriched for low-molecular-weight peptide fractions and directed at the corresponding human tissue.
Our Thyroid Bioregulator, also identified as Thyreogen or Peptide Complex A-2, sits in that class. It is a dietary supplement intended to support healthy thyroid gland cells, metabolic balance, and endocrine wellness. It is not a T4 or T3 replacement, and it is not sold as one.
If a lab report on a Cytomax capsule came back listing 38 mcg of T4, it would no longer be a bioregulator. It would be a hormone product.
The Proposed Mechanism
Short peptides are small enough to cross membranes that larger proteins cannot. Khavinson, Lin’kova and Tarnovskaya built spatial models of DNA-peptide complexes for 19 short peptides using molecular docking, proposing that short peptides penetrate the cytoplasmic and nuclear membranes and bind DNA directly. Their framing is careful: one short peptide can regulate dozens of genes, and the molecular mechanism remains unclear.6

That is a proposal supported by modeling, not a demonstrated pathway, and it is worth stating in those terms. It is also a fundamentally different kind of claim from hormone replacement. The peptide is not supposed to occupy the thyroid hormone receptor. It is supposed to look like a fragment the tissue already recognizes.
What The Animal Research Actually Shows
This is where most write-ups on this subject overreach. We’ve read the studies and will explain what we think.
A series of experiments by Kuznik and colleagues tested two tetrapeptides, Lys-Glu-Asp-Gly and Ala-Glu-Asp-Gly, in birds whose pituitary had been surgically removed. Hypophysectomy produced atrophy of the thyroid and secondary hypothyroidism. Administering the tetrapeptides for 40 days significantly reduced those changes and raised TSH, T3 and T4.78 The effect was weaker in old hens than in young chickens.9
Two things need saying about those papers.
First, those tetrapeptides were synthesized from the amino acid composition of pituitary extracts, not thyroid extracts. The thyroid in those experiments is downstream. The peptide restores the signal from above and the gland recovers. That is evidence about the hypothalamic-pituitary-thyroid axis responding to short peptides. It is not evidence about A-2 specifically, and anyone telling you otherwise has not read the studies.
Second, birds are not people, and 40 days of injection in a hypophysectomized chicken is a long way from a capsule taken with breakfast.
The closest human work on a thyroid-tissue peptide is Gorbachev and colleagues in 2005, working with residents of the Magadan Region, where age, climate and local biogeochemistry all strain the thyroid. They used Thyramin, a thyroid-tissue peptide preparation, in people with reduced thyroid function, describing a tissue-specific effect on thyroid cells and restoration of disturbed function.10
Two caveats belong in the body text rather than a footnote. Thyramin is a cytamin-class preparation from the same research school, and Cytomax products were developed later as a cleaner, lower-molecular-weight fraction. They are relatives, not the same capsule. And this is one regional clinical paper published in Russian, not a multicenter trial against levothyroxine.
A 2026 review of peptide strategies in thyroid care reaches the same broad conclusion from outside the bioregulator literature: peptide work relevant to the thyroid is largely mechanistic, preclinical, or early exploratory, and thyroid-specific randomized trials remain scarce.11
 View the Thyroid Bioregulator
Desiccated Thyroid vs Bioregulator, Side By Side
Why “Natural” Is Not A Useful Referee
Both products can claim natural origin. One is a whole gland ground up. The other is a peptide fraction of a gland. Neither description tells you the thing you need to know.
“Natural” does not tell you whether you are swallowing T3. It does not tell you whether the feedback loop is being overridden or supported. It does not tell you whether a pregnant woman should be near the bottle.
Mechanism is the better referee. Desiccated thyroid changes the hormone pool delivered to every thyroid hormone receptor in the body. A Cytomax changes the peptide signal delivered to thyroid tissue, on the experimental claim that homologous short peptides help that tissue do its own work.
If your TSH is 12 and your free T4 is below range, you do not have a peptide-signaling preference. You have hypothyroidism and you need a clinician. If your labs are stable and the question is how to support the gland you still have, a peptide complex is at least asking a different question.
What Else Actually Moves The Gland
Neither product substitutes for the raw materials of hormone synthesis. Iodine is the substrate. Selenium sits in the deiodinases that convert T4 to T3 and in the selenoproteins that protect follicular cells from the hydrogen peroxide thyroperoxidase generates. Iron is required for thyroperoxidase itself, and inadequate iron status can impair hormone synthesis even when iodine supply is adequate.2 Iodine intake itself varies widely by region and dietary pattern, and both deficiency and excess carry consequences.12
A peptide signal cannot invent iodide that is not in the diet. A grain of desiccated thyroid cannot repair a selenium-depleted deiodinase system.
Which is why a serious thyroid plan still looks ordinary. Check TSH and free T4 with a clinician. Look at antibodies if autoimmunity is on the table. Fix iron and sleep. Then decide what, if anything, is missing.
The Short Version
Desiccated thyroid is dried gland used as a T4-plus-T3 drug, with randomized crossover data in diagnosed hypothyroidism and a live guideline debate attached to its T3 content. A thyroid Cytomax is a peptide fraction used as a tissue signal, with mechanistic modeling, animal work on the HPT axis, and one regional human study behind it.
Use the drug when the gland cannot meet the body’s hormone demand. Consider the bioregulator when the question is how to support the gland you still have. If both questions are open at once, that is a clinician visit, not a forum poll.
View the Thyroid Bioregulator | Read the thyroid research index | Take the Bioregulator Quiz
References
- Armour Thyroid (thyroid tablets, USP) prescribing information. FDA label.
- Köhrle J. Selenium, Iodine and Iron: Essential Trace Elements for Thyroid Hormone Synthesis and Metabolism. Int J Mol Sci. 2023;24(4):3393. PMC (PMID 36834802).
- Hoang TD, Olsen CH, Mai VQ, Clyde PW, Shakir MK. Desiccated thyroid extract compared with levothyroxine in the treatment of hypothyroidism: a randomized, double-blind, crossover study. J Clin Endocrinol Metab. 2013;98(5):1982-1990. PubMed.
- Shakir KMM, Brooks DI, McAninch EA, et al. Comparative Effectiveness of Levothyroxine, Desiccated Thyroid Extract, and Levothyroxine + Liothyronine in Hypothyroidism. J Clin Endocrinol Metab. 2021;106(11):e4400-e4413. PubMed.
- Jonklaas J, Bianco AC, Bauer AJ, et al. Guidelines for the Treatment of Hypothyroidism: Prepared by the American Thyroid Association Task Force on Thyroid Hormone Replacement. Thyroid. 2014;24(12):1670-1751. PMC.
- Khavinson VKh, Lin’kova NS, Tarnovskaya SI. Short Peptides Regulate Gene Expression. Bull Exp Biol Med. 2016;162(2):288-292. PubMed.
- Kuznik BI, Pateyuk AV, Rusaeva NS. Effect of tetrapeptides Lys-Glu-Asp-Gly and Ala-Glu-Asp-Gly on the structure and function of the thyroid gland in neonatally hypophysectomized chickens. Bull Exp Biol Med. 2008;145(1):104-107. PubMed.
- Kuznik BI, Pateyuk AV, Rusaeva NS, Baranchugova LM, Obydenko VI. Effects of peptides Lys-Glu-Asp-Gly and Ala-Glu-Asp-Gly on hormonal activity and structure of the thyroid gland in hypophysectomized young chickens and old hens. Bull Exp Biol Med. 2011;150(4):495-499. PubMed.
- Kuznik BI, Pateiuk AV, Rusaeva NS, Baranchugova LM, Obydenko VI. Effects of Lys-Glu-Asp-Gly and Ala-Glu-Asp-Gly peptides on hormonal activity and thyroid morphology in hypophysectomized mature and old birds. Adv Gerontol. 2011;24(1):93-98. PubMed (Russian).
- Gorbachev AL, Lugovaia EA, Ryzhak GA, Khavinson VKh. Peptide bioregulator efficacy in the correction of reduced thyroid gland function in the residents of Magadan Region. Adv Gerontol. 2005;16:80-87. PubMed (Russian).
- Mazza AD. Peptide Therapies in Thyroid Health: Emerging Applications in Endocrine and Immune Modulation. Integr Med (Encinitas). 2026;25(2):29-37. PubMed.
- Bath SC. Thyroid function and iodine intake: global recommendations and relevant dietary trends. Nat Rev Endocrinol. 2024;20(8):474-486. PubMed.
